
ENERGY SCIENCE
Our TSEE guest writer Pascal Mensah is a physician specializing in Clinical Immunology, Immunometabolism, and Integrative & Regenerative Medicine at Juaneda Hospital (Mallorca, Spain). In this post, he draws on fifteen years of treating autoimmune disease
to argue that inflammation may be better understood as a problem of energy flow
than as a problem of immune signaling alone.

In a single week of clinic, I may see a woman with lupus, a young man with Crohn’s disease, and a patient whose rheumatoid arthritis is changing the shape of her hands.
Three diagnoses. Three specialties. Three sets of guidelines.
And yet inside them I keep finding the same thing: inflammation that will not resolve.
The Question That Keeps Coming Back
I have been working on autoimmune disease for nearly fifteen years. Across conditions that look nothing alike, inflammation has been the common thread.
We have not been idle. Medicine has developed a myriad of treatments. Corticosteroids, immunosuppressants, and monoclonal antibodies that block a single cytokine (signaling protein) with a precision that would have seemed like science fiction when I started. Some have been genuine successes. I have seen patients recover lives they had given up on.
But I have never been convinced that we could solve inflammation with one product, or two.
Blocking a cytokine treats the immediate message. It often does not treat the reason the message is being sent.
Patients respond, then, at some point, stop responding. We switch targets, escalate, and combine. The inflammation moves rather than resolves. I began to suspect we were describing the fire by its smoke.
Why I Started Bringing Physics Into Immunology
If we want to understand inflammation, I think we have to bring physics into biology—and especially into immunology.
My reason is simple. Mitochondria determine the fate and function of an immune cell, including which cytokines it can produce. And, among their various functions, mitochondria are energy-transformers. Importantly, their energy transformation activities are bound by physics.
In doing so, they shape how cells transform energy, move electrons, and maintain the conditions required for life. Biology is not reducible to physics, but it unfolds within physical constraints.
That is what drew me to the Energy Resistance Principle described by Picard and Murugan in a previous post. It treats a cell as an electrical–energetic circuit: electrons from our food flux through the carbon wiring of metabolism toward oxygen, the terminal acceptor.
Energy resistance (éR) is whatever impedes that flow. Some resistance is necessary for useful work to get done. Without any resistance, an electron’s potential could never become cellular fuel in the form of ATP (adenosine triphosphate).
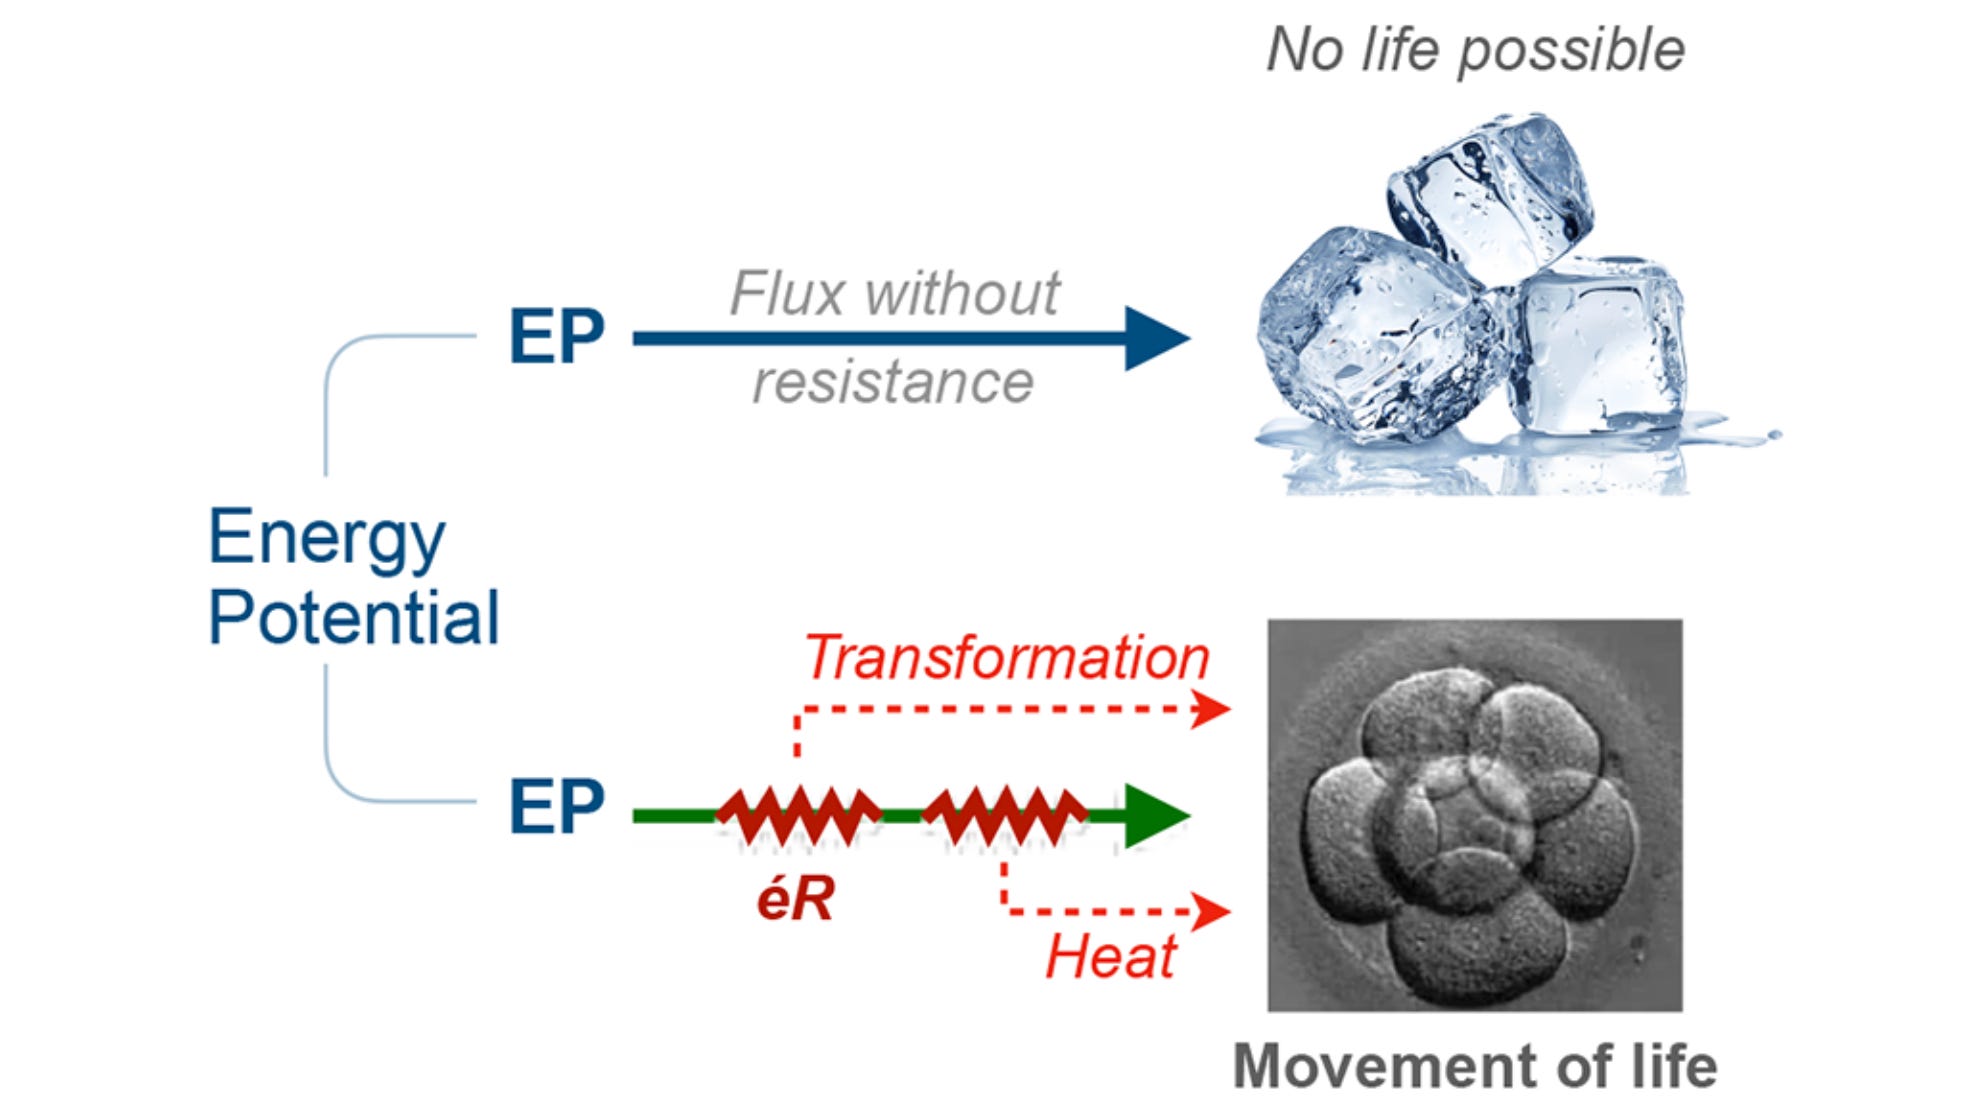
But when resistance climbs too high, energy stalls and dissipative losses rise: oxidative and reductive stress, heat, molecular damage, inflammation, and lost information. These are the hallmarks of disease and aging.
This changed the question I ask in the clinic. Instead of “which cytokine is too high?”, I began asking what is the cause of excess resistance in this patient, and why?
Cytokines as Alarms, Not Villains
In this framing, the immune system both reports energy resistance and corrects it. Pro-inflammatory cytokines are the reporting arm. They are the alarms that let your body know resistance has risen.
The trigger is mitochondrial. When the electron transport chain is impeded, electrons back up, membrane potential becomes abnormal, and reactive oxygen species leak from Complexes I and III, the structures that carry out energy transformation. Those leaked species are a recognized “signal 2” that drives pathways that raise pro-inflammatory output. The cytokines we measure in blood report on the impedance underneath.
High energy resistance → more reactive oxygen species leaked → more inflammatory cytokines released
The same logic extends to endocrine signals. The cytokine GDF15 carries word of energetic distress to the brainstem. There, high circulating GDF15 levels serve as an index of high resistance. This “alarm” prompts the body to conserve energy through loss of appetite and fatigue. The balance between alarms like GDF15 and anti-inflammatory correctors conveys the net resistance of the system.

The Role of Mitochondria in Maintaining Balance
This is where the framework stopped being a metaphor for me. Mitochondria are not merely permissive for regulatory cytokine production. They are required.
The clearest evidence comes from regulatory B cells, or Bregs, a subset of B cells that produces interleukin-10 (IL-10), a powerful anti-inflammatory cytokine central to this story. Unlike conventional B cells, they differentiate appears to depend on intact mitochondrial electron transport and tightly regulated, homeostatic levels of reactive oxygen species.
So what happens if we inhibit Complex I or Complex III with a drug? The mitochondrial membrane depolarizes, and there is a sharp, selective drop in production of anti-inflammatory cytokines like IL-10.
Inhibiting Complex I or Complex III does not directly affect production of the pro-inflammatory cytokines. Only the anti-inflammatory, resistance-lowering arm collapses.
What is lost is the ability to answer the alarm, not to set it off. A cell cannot make IL-10 unless its electron transport chain is already healthy—by definition, a low-resistance state.
There is a clinical echo. In patients with lupus who have depolarized Breg mitochondria, elevated reactive oxygen species, and fewer thioredoxin-producing B cells, giving the antioxidant thioredoxin restored both membrane polarization and Breg numbers.— This suggests thioredoxin may help regulate the éR set point.
What It Costs to Run a Cell
This is where physics becomes important in the story.
For an electron current (I) flowing through resistance (R), the power dissipated as heat is P = R·I².
That is Joule’s law. It’s why a wire warms up when current fights its way through. Resistance is the term that converts useful flux into wasted heat and entropy. Loosely, entropy is the disorder in a system. Energy resistance is the biological version of that term.
The mechanism by which IL-10 would lower it is well defined. In immune cells called macrophages, IL-10 signalling results in the breakdown and recycling of damaged mitochondria leaking reactive oxygen species and dissipating heat. And respiratory capacity is restored. Both reduce the back-up of electrons—the I²R term—lowering the cost of running the cell.
I have a prediction that has not yet been tested. Because entropy production is related to aging dynamics and lifespan, chronic IL-10 signalling should measurably reduce the entropy produced per unit of ATP.
It is also falsifiable: in cells engineered so they cannot break down damaged mitochondria, IL-10 should not lower energy resistance at all. If it does, my prediction is wrong.
IL-10 as a Thermostat, Not a Brake
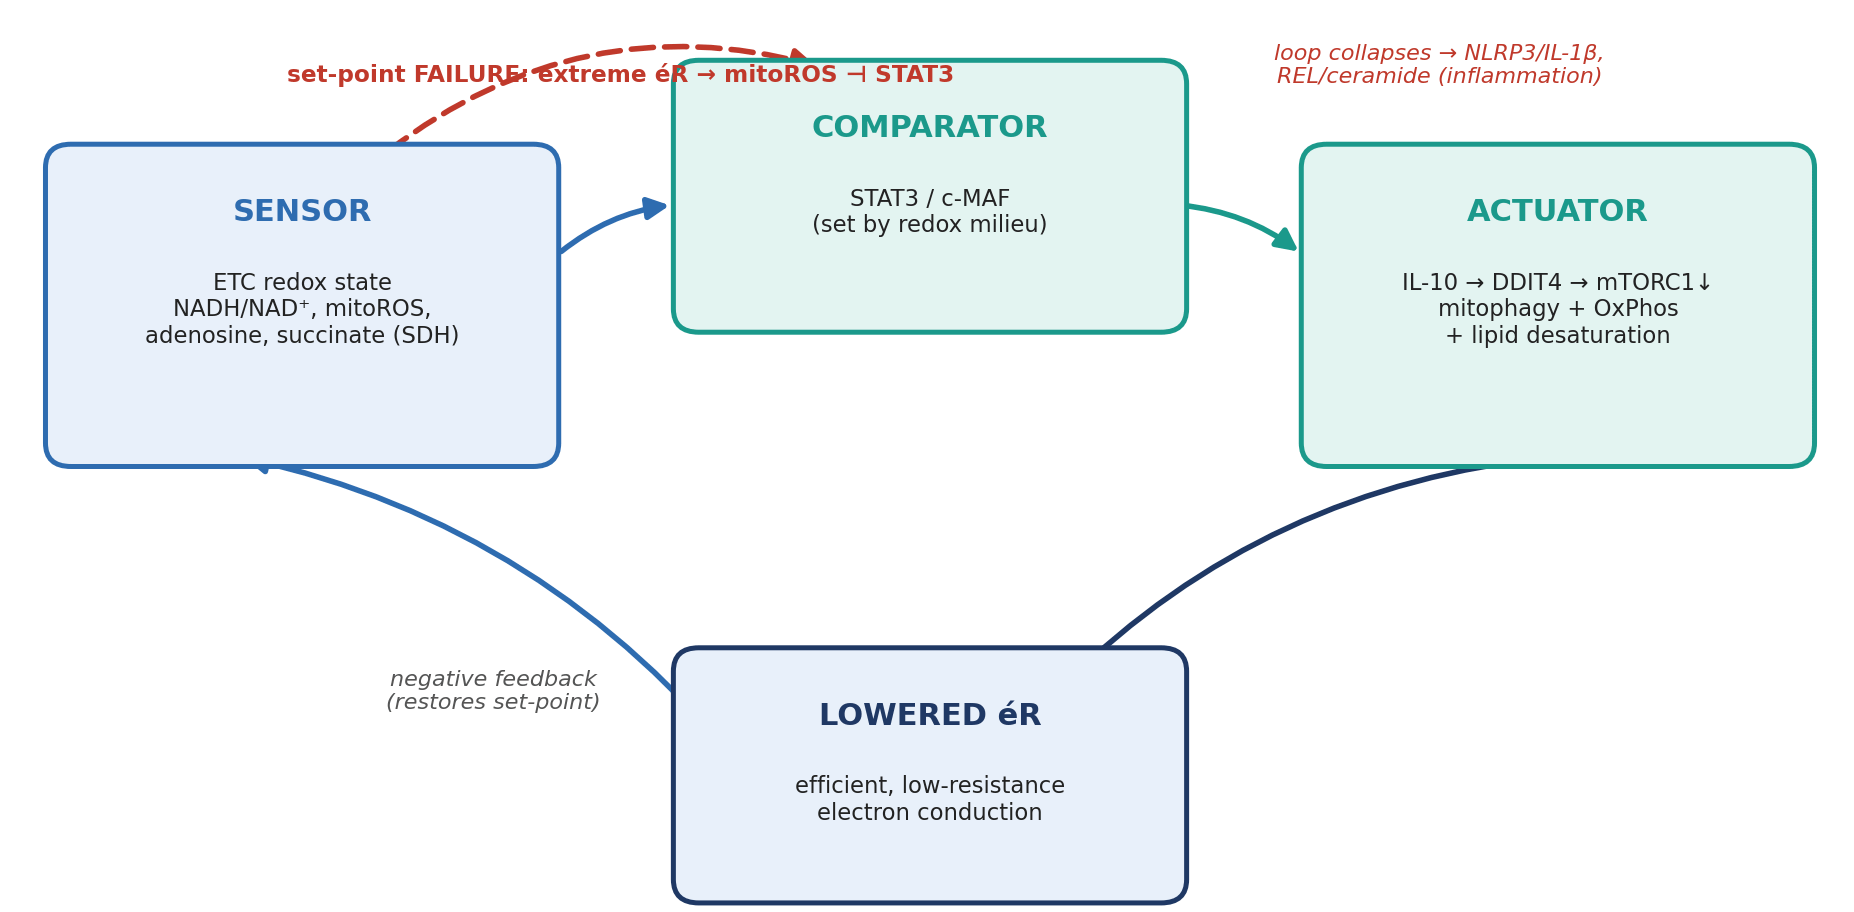
We usually describe IL-10 as the anti-inflammatory brake. I have come to think of it as a thermostat that calms inflammation by improving how the cell handles energy.
It does this in at least two ways. The first is the mitochondrial clean-up just described. The second involves fats. IL-10 supports production of monounsaturated fatty acids, the flexible fats that keep membranes fluid. When IL-10 is lost, stiffer saturated very-long-chain molecules called ceramides accumulate instead. This hampers mitochondrial respiration and keeps inflammation switched on through a gene-control protein called REL. Restoring the monounsaturated fats reverses it—a metabolic correction, not an immunological one.

It also reframes what happens when IL-10 fails altogether, for example, in the severe enterocolitis (inflammatory bowel disease) caused by a non-functional IL-10 receptor. The problem is not only a missing brake; it is the lost control over energy resistance itself. A shortage of IL-10 can lead to unrestrained mitochondrial resistance. The downstream signature is the “cytokine storm”: a dangerous reaction, driven by the release of too many cytokines at once. It can cause high fever, organ failure, and death.
What This Changes in the Clinic
Reading inflammation as a disorder of energy-resistance control shifts the logic from “add an anti-inflammatory drug” to “lower the resistance.” Those sound similar, but they are not.
Rather than flooding the body with IL-10 from the outside, the better strategy may be to support the cell’s own thermostat.— Supplying a thermostat’s output is not the same as repairing it.
There are two potential approaches: adopt a diet favouring monounsaturated fats over the stiff ceramides that impair mitochondria, and repair of the control points that let cells produce IL-10 and respond to it.
It is also where the framework becomes measurable The GDF15 to IL-10 ratio, alarm over correction, is a plausible clinical index of net energetic resistance.
Measures That Could Reflect Energy Resistance
Energy resistance cannot be measured directly, so clinicians would need a panel of multiple measures rather than just one marker.
The panel could include:
plasma GDF15 against the IL-10 signalling reserve in a patient’s B cells;
spare respiratory capacity, membrane potential and mitochondrial reactive oxygen species by extracellular-flux respirometry; and
the thioredoxin set point as a proxy for metabolic reserve.
All thresholds would be illustrative, and the panel would be best measured repeatedly over time. Still, these markers only hint at energy resistance—they do not measure it directly.
What I Still Do Not Know
This is a synthesis, rather than a direct demonstration. Each component is experimentally supported: mitochondrial function is required for IL-10 production, reactive oxygen species can amplify inflammatory signalling, and this response engages downstream lipid programs. What remains to be tested is the unifying idea that cytokines may, in part, report on a shared energetic state.
Several questions remain open. Does this set point differ across autoimmune diseases, or does a common underlying problem manifest in different tissues? Can it shift with something as ordinary as sleep, meal timing, or exercise? And when a patient no longer responds to a monoclonal antibody, have we quieted the signal while the underlying resistance continues to rise?
What fifteen years in autoimmune medicine has taught me is that we have become very good at silencing the alarms. Whether we can lower the resistance that sets them off is, to me, the far more interesting question.
If it is, then inflammation is not only an immunological problem. It is an energetic one, and it may need to be treated as such.
We’re excited to be assembling a community around the Science and Experience
of Energy with this Substack. We hope to bring people together to reflect on
connections between energy science and the human experience.
If this post resonated with you, please consider sharing it with others.
When you inhibit Complex I or III, the inner mitochondrial membrane (IMM) depolarizes. Pro-inflammatory cytokines do not drop. Why? Because the inflammatory cascade is an evolutionary backup plan (atavism). It runs on primitive, disordered, high-entropy pathways like cytoplasm glycolysis and fermentation. It requires zero magnetic alignment. The High-Voltage Handshake: To synthesize and secrete IL-10, a Breg must actively maintain an exceptionally low-resistance state (éR) across its electron transport chain. It requires intact electron flow to generate the precise electromagnetic and Ultra-weak Photon Emission (UPE) fields that instruct the nucleus to open the IL-10 gene promoter. The Selective Collapse: The moment the IMM drops its negative voltage, the cell ALSO loses its capacity for isotopic fractionation. Heavy deuterium (²H) floods the matrix, the water lattice de-structures into thick sludge, and the high-energy cost of maintaining peace can no longer be met. The cell can still scream (inflammation), but it can no longer enforce order (IL-10). Regarding lupus you did not take the physics lesson far enough. Thioredoxin is not just a chemical antioxidant; it is a vital protein semiconductor that acts as an electron donor pool for the cell. Lowering the Resistance Set Point: When exogenous thioredoxin is introduced into these depolarized Bregs, it manually floods the system with missing electrons. Because light and field stabilization can only interact with electrons, this influx of electronic charge density instantly stabilizes the radical pair spins at Complex I and III. This is what Vitamin D from the sun does. It slows ECT before CCO. Restoring the Battery: The localized spin chaos is quieted, allowing the IMM to remagnetize, rebuild its negative exclusion zone water battery, and repolarize its membrane. The éR set point drops, the Breg numbers recover, and the cell can finally resume its high-energy production of IL-10. This mechanism explains why modern non-native EMFs (nnEMF) and artificial blue-pumped LEDs are the direct, upstream drivers of the global explosion in autoimmune conditions like lupus, rheumatoid arthritis, and Graves' disease. High-frequency wireless radiation and screen glare scramble the Zeeman splitting effect in the mitochondrial heme proteins. This destroys the seasonal calibration of the PER2 lipid raft mechanics. The Calcium Flood: As the lipid rafts lose their structural tensegrity, voltage-gated calcium channels leak constantly. Calcium ions flood the matrix. Because calcium is a heavy dopant atom, an unregulated flood inside the mitochondrion physically binds to and blocks the electronic active sites of Complex I and Complex III. The Immune Trap: This environmental blockade induces the exact same depolarization seen in the drug studies. The resistance-lowering, anti-inflammatory arm collapses across your entire white blood cell pool. Your immune system remains stuck in a permanent, uncoupled state of chronic alarm, unable to manufacture the T-Regs or Bregs needed to establish peripheral tolerance.
So I guess "take two aspirins and call me in the morning" doesn't really cut it, anymore.